Understanding the Anion Gap Measures
The anion gap is a straightforward yet effective way to examine serum chemistry and identify whether there may be surplus unmeasured anions in the blood. It is calculated from common electrolytes on a routine electrolyte panel, especially sodium and chloride, with bicarbonate usually included as well. In many cases, the anion gap helps explain acid-base status and indicates a hidden disorder even before symptoms become obvious.
At its core, the anion gap shows the difference between measured positive and negative ions in the bloodstream. Because sodium is the major measured cation and chloride and bicarbonate are the major measured anions, changes in these values can show whether something is missing from the balance. A higher-than-expected gap often implies added acids or other unmeasured substances. That is why an anion gap can be informative even when the rest of the panel looks familiar.

The concept is especially valuable in clinical interpretation because it offers a window into acid-base balance. While the body uses buffer systems to keep pH stable, changes in laboratory values can show early or subtle problems. A normal bicarbonate level does not automatically mean everything is fine, and understanding the anion gap helps link blood test results with possible physiologic changes.
How to Operate an Anion Gap Calculator
An Anion Gap Calculator streamlines the math, but it is still important to know the underlying calculation formula. The most common version is:
Anion gap = sodium - (chloride + bicarbonate)
Some clinicians also include potassium in the formula, though many routine calculations exclude it because potassium contributes less to the final number. When potassium is included, the formula becomes slightly different, but the basic interpretation remains similar. The calculator is only as useful as the values entered, so confirm the numbers from the electrolyte panel before drawing conclusions.
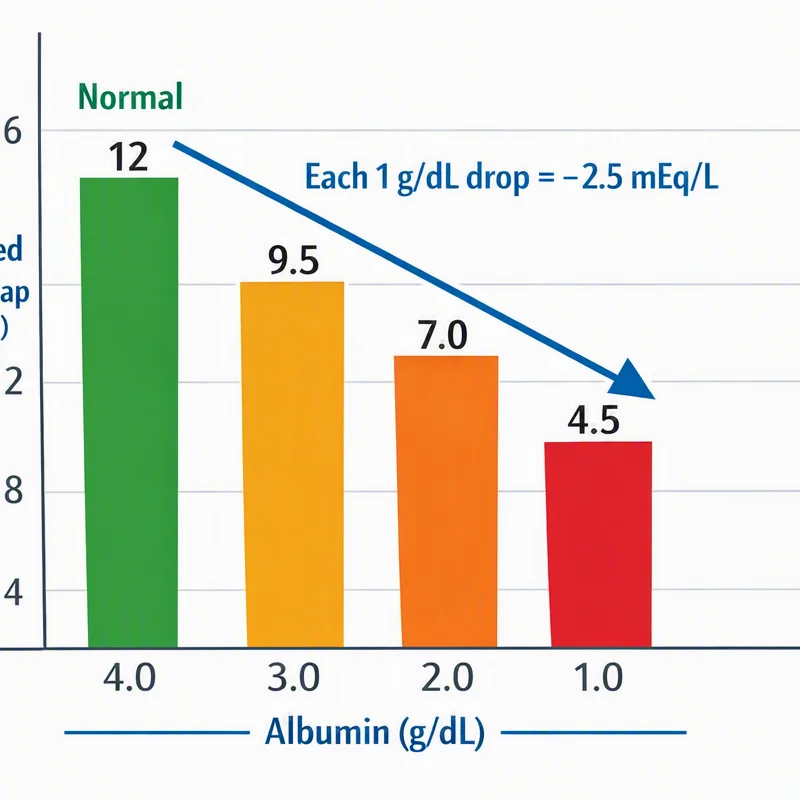
When using an Anion Gap Calculator, pay close attention to whether the result is reported as a standard gap or an adjusted calculation. For example, low albumin can make the gap appear falsely normal. Many calculators therefore allow an albumin correction so that the corrected anion gap better matches the true acid burden. This matters in diagnostic assessment because a normal-looking number may hide clinically relevant anion gap elevation.
The practical approach is simple:
- Enter the measured values for sodium, chloride, and bicarbonate. Verify whether potassium is part of the formula being used. Examine albumin and apply correction if needed. Match the result with the lab’s reference range. Read the number in the context of symptoms and other laboratory values.
Using the calculator well is not just about arithmetic. It is about correlating the result with clinical correlation, overall acid-base interpretation, and the broader picture of possible systemic illness.
Typical bicarbonate: Why exactly the Value Can Still Carry weight
A normal bicarbonate value commonly puts at ease clinicians and individuals, but it may not rule out an acid-base disorder. The body can briefly compensate, and that adjustment may keep bicarbonate in the normal range even while an subtle process is developing. This is what makes an elevated anion gap with normal bicarbonate warrants thorough review rather than dismissal.
One reason this happens is metabolic compensation. The body may be compensating for an acid load through respiratory or renal pathways, masking a more significant problem in the background. Another possibility is a mixed disorder, where one process raises the anion gap while another process shifts bicarbonate higher or down, creating a result that looks falsely normal. In other words, normal bicarbonate does not always mean normal physiology.
Think of bicarbonate as one part of the broader acid-base puzzle. It is essential, but only part of the picture. If the Anion Gap Calculator indicates an abnormal value, that may signal a underlying disorder even when bicarbonate appears steady. This is especially useful when evaluating systemic acidosis or other conditions that can progress before classic laboratory changes fully appear.
For that reason, the anion gap should be read as part of overall clinical interpretation. It can help uncover early or partially compensated metabolic acidosis, especially when the pattern of serum chemistry indicates something is not making sense.
Common Reasons of an Elevated Anion Gap with Normal Bicarbonate
An elevated anion gap with normal bicarbonate can appear in several important conditions. The key is not to assume the result is benign simply because bicarbonate remains within range. The following causes are typical and clinically relevant.
Lactic acidosis can elevate the gap when lactate accumulates due to poor tissue oxygen delivery, severe illness, medications, or other stressors. Early in the process, bicarbonate may still look acceptable if compensation is active or if the acid load is still building. This is one reason the anion gap may provide an earlier clue than bicarbonate alone.
Ketoacidosis is an additional classic cause. In diabetes, starvation, alcohol use, or other metabolic stress states, ketones can accumulate and create an anion gap elevation. If the process is early or mixed with another alkalinizing influence, bicarbonate may not yet fall below the normal range. The result can still signal a clinically important acid-base problem.
Renal failure can also raise the anion gap because the kidneys cannot clear acid effectively. As retained acids build up, the gap may rise before bicarbonate drops significantly. In chronic or evolving kidney dysfunction, this pattern may be subtle and requires close attention to the rest of the electrolyte panel and renal function markers.
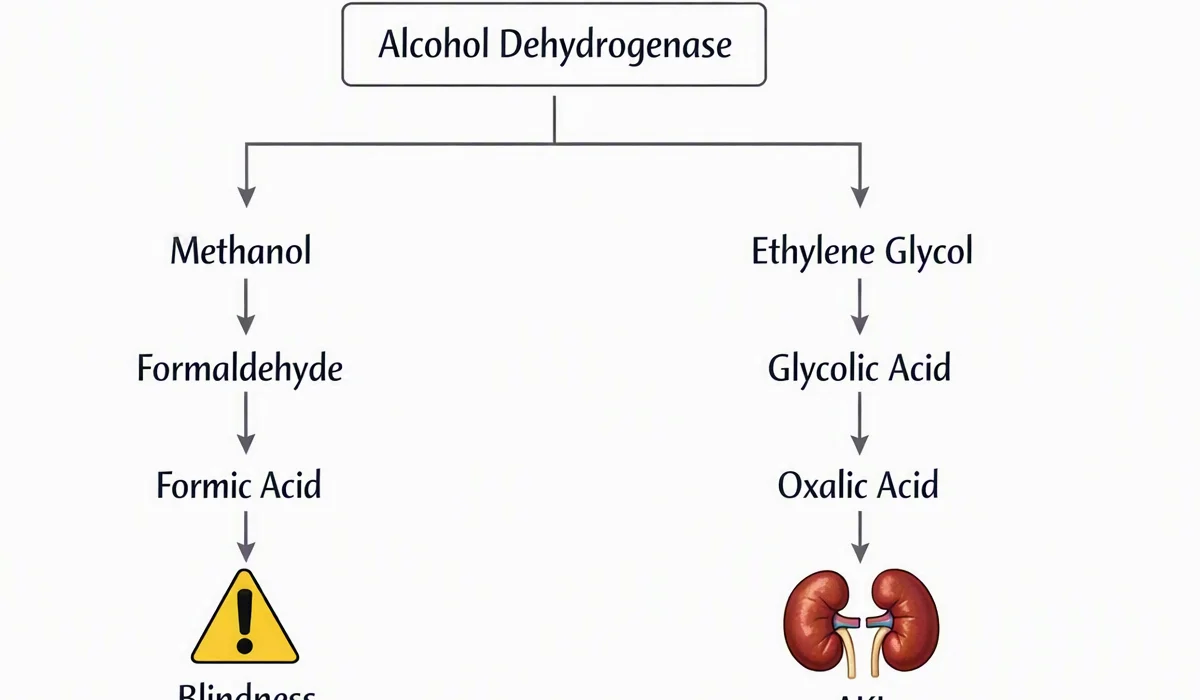
Toxic alcohols are a vital consideration because they can produce a dangerous high-gap state. Methanol, ethylene glycol, and related substances can generate acid metabolites that increase the gap even before other classic abnormalities fully emerge. This is a situation where timely recognition matters because the clinical consequences can be severe.
These causes highlight why a normal bicarbonate does not necessarily mean a normal acid-base state. The gap can point toward an early, evolving, or partially masked process that needs a more detailed diagnostic assessment.
Albumin Correction and the Revised Anion Gap
Albumin is one of the most important factors affecting the anion gap. Because albumin is a negatively charged protein, reduced albumin can decrease the measured gap and obscure clinically important abnormalities. This is why hypoalbuminemia can lead to underrecognition of an acid-base problem if the result is not adjusted.
The corrected anion gap is an adjusted calculation that takes into account low serum albumin. If albumin is below normal, the uncorrected gap may look falsely reassuring, even though unmeasured acids are present. In practice, albumin correction enhances the accuracy of clinical interpretation and helps clinicians compare the result against the appropriate anion gap reference range.
Why does this matter so much? Because hypoalbuminemia is often seen in hospitalized and chronically ill patients. If albumin is low, the measured gap can miss the degree of anion gap elevation. A corrected value may expose hidden metabolic acidosis that would otherwise be missed. That is especially important when evaluating complex illness, where several disorders may coexist.
Albumin correction is not a minor detail. It is a critical component of proper acid-base interpretation. Any serious review of anion gap findings should include serum albumin, the expected reference range, and the possibility that the corrected result tells a different story entirely from the raw number.
Step-by-Step Assessment Workflow
A trustworthy assessment starts with a structured approach. The objective is to advance from numbers to insight without missing key steps. This is especially important when bicarbonate is still normal, because the pattern can be deceptive if read too quickly.
Step 1: Check the blood chemistry panel. Start with the electrolyte panel and verify sodium, chloride, bicarbonate, and potassium. Confirm the values are up-to-date and internally coherent. A small measurement error can change the https://anion-gap-chart717.evergrovio.com/posts/original-vs-adjusted-anion-gap-what-changes outcome.
Second step: Determine or confirm the anion gap. Follow the calculation formula or an Anion Gap Calculator. Note whether potassium is included. Compare the result with the lab’s reference range.
Step three: Review albumin. If serum albumin is low, derive the corrected anion gap. This is vital in hypoalbuminemia and can uncover a hidden disturbance.
Step 4: Search for acid-base evidence. Examine the arterial blood gas if available. The arterial blood gas helps identify pH, respiratory compensation, and whether there is a concurrent respiratory or metabolic process. Along with bicarbonate, it helps define the broader acid-base status.
Step 5: Consider the delta gap. The delta gap can help identify a mixed disorder by comparing the change in anion gap with the change in bicarbonate. If the values do not move in the expected direction, another acid-base process may be present.
Step six: Combine the clinical context. This is where clinical correlation plays the biggest role. Symptoms, medications, kidney function, diabetes, alcohol exposure, and hemodynamic status all help clarify whether the result reflects lactic acidosis, ketoacidosis, renal failure, toxic alcohols, or another cause.
This workflow turns a simple lab result into a meaningful diagnostic assessment. It also minimizes the chance of missing a hidden disorder when bicarbonate remains in the normal range.
Constraints & Pitfalls of Anion Gap Calculations
Even though the anion gap is useful, it has significant drawbacks. A key issue is lab variation. Different laboratories may use slightly different procedures, instruments, or reporting practices, which can shift the apparent reference interval. A result that is slightly abnormal in one setting may be interpreted differently in another.
Measurement error is another concern. Subtle differences in sodium, chloride, or bicarbonate can substantially affect the gap. That means the calculated number should never be interpreted in isolation. Repeat testing may be needed if the result does not fit the clinical picture.
There are additionally broader diagnostic limitations. The anion gap does not directly measure all acids or distinguish among every cause of metabolic acidosis. It can suggest a problem, but it cannot define the exact cause without further evaluation. That is why it should be paired with clinical interpretation, arterial blood gas findings, and the patient’s overall presentation.
One more pitfall is overconfidence in a normal result. A normal gap does not always exclude an acid-base issue, especially if hypoalbuminemia is present or if there is a mixed acid-base state. Likewise, a mildly elevated gap does not automatically mean a severe disorder. The number is a clue, not a diagnosis.
When to Pursue Medical Assessment
An atypical anion gap should be considered with the patient’s condition in mind. If there are worrisome symptoms such as shortness of breath, disorientation, significant weakness, emesis, volume depletion, thoracic discomfort, or altered mental status, medical evaluation should not be delayed. These can be indications of metabolic acidosis or a different serious condition.
Immediate evaluation is especially important when the result points to an electrolyte abnormality or possible poisoning. Increased-gap patterns linked to lactic acidosis, ketoacidosis, renal failure, or toxic alcohols may require urgent treatment. The earlier the cause is identified, the better the chance of avoiding complications.
Even without severe symptoms, an elevated or unexplained result warrants review by a clinician if it remains, worsens, or conflicts with the rest of the laboratory data. This is particularly true when the Anion Gap Calculator shows an abnormality despite normal bicarbonate, because that pattern can indicate an developing or partially adjusted disorder.
Common Questions
What does an elevated anion gap with normal bicarbonate mean?
It often means there may be an acid-base issue that is not yet obvious on bicarbonate alone. This can happen with early metabolic acidosis, a mixed disorder, or compensation that is temporarily keeping bicarbonate in the normal range. A clinician should assess the full clinical interpretation, including symptoms, albumin, and other laboratory values.
What is the correct way to calculate the anion gap?
Use the calculation formula: sodium minus the sum of chloride and bicarbonate. Some methods also include potassium. An Anion Gap Calculator can do the math for you, but the values must come from a reliable electrolyte panel. Always compare the result with the appropriate reference range.
Why is albumin play a role when reading the anion gap?
Albumin is a key unmeasured anion, so low albumin can make the gap appear falsely normal. In hypoalbuminemia, the corrected anion gap gives a better picture of the true acid burden. Albumin correction is an integral part of an adjusted calculation and strengthens acid-base interpretation.
Can normal bicarbonate eliminate acid-base disorders?
No. A normal bicarbonate value does not fully rule out an acid-base disorder. Compensation, early disease, or a mixed process can keep bicarbonate in range while the anion gap is still elevated. That is why the overall acid-base status should be assessed with the arterial blood gas, albumin, and other laboratory findings.
When should an anion gap result be evaluated by a clinician?
Any unexplained abnormal result should be reviewed, especially if there are symptoms, concern for metabolic acidosis, or possible electrolyte imbalance. Urgent evaluation is important if toxic exposure, severe illness, or worsening confusion is present. A clinician can place the number in the right clinical context and decide whether additional testing is needed.