Absolutely, dehydration can impact the anion gap, but generally indirectly. The main issue is that fluid loss can alter blood volume and cause concentration variations in lab values, which may cause the result look different without necessarily meaning there is a harmful metabolic problem. An Anion Gap Calculator can assist you to estimate the number, but clinical interpretation depends on the full picture, including the electrolyte panel, serum bicarbonate, albumin, and symptoms.
This difference matters. A changed result may reflect simple hemoconcentration from fluid loss, or it may point to a true acid-base issue such as metabolic acidosis. Knowing the difference helps you know when the result is likely temporary and when it needs a closer look.
Understanding the Anion Gap?
The anion gap is a calculated figure used in clinical chemistry to help evaluate acid-base balance. It is not a directly recorded value. Instead, it indicates the difference between routinely measured electrically charged particles, especially sodium and chloride, along with bicarbonate in many formulas. This makes it a useful diagnostic marker for certain forms of metabolic disturbance.
In plain language, the anion gap helps clinicians detect unmeasured substances in the blood. If the gap is elevated, it can suggest extra acids are present. If it is lower than expected, it may suggest low protein levels, lab issues, or less unmeasured positive ions than usual.
The exact reference range can vary depending on the lab and the method used. That is why clinical interpretation should always use the result from the same testing facility or a trusted medical testing source rather than a fixed number.
The main components behind the calculation are part of routine serum electrolytes. Because these are commonly included in a basic metabolic panel or a broader electrolyte panel, the anion gap is often available even when it is not ordered as a separate test. That makes it a convenient tool for assessing blood chemistry and spotting abnormal results.
How an Anion Gap Calculator Functions
An anion gap calculator uses the values from a blood panel to estimate the gap fast. Most calculators rely on sodium, chloride, and serum bicarbonate. Some formulas also factor in albumin, because albumin is a important unmeasured anion and can significantly influence the result.
The usual logic is simple: the calculator performs an anion calculation by comparing the measured cations and anions in the sample. When bicarbonate is low, the gap often increases because bicarbonate is being depleted or lost while unmeasured acids accumulate. When albumin is low, the gap may appear lower than expected even if the true acid-base state is more involved.
This is why a calculator is useful, but not sufficient. It provides a numerical estimate, not a diagnosis. The result must be interpreted alongside the electrolyte panel, the basic metabolic panel, and the patient’s overall condition. In other words, the calculator is best used as part of supportive assessment, not as a single answer.
Albumin deserves particular attention. Because it carries negative charge, low albumin can lower the measured gap. Many clinicians will consider a correction when hypoalbuminemia is present, since failing to account for it can hide a important high anion gap.
Can Dehydration Change the Anion Gap?
Fluid loss can change the anion gap, but the effect is often due to fluid loss and concentration changes rather than a direct change in acid production. When plasma volume decreases, some blood components become more concentrated. That can skew laboratory results on a blood draw and make results look more abnormal than they would after rehydration.
In slight dehydration, the anion gap may not shift much at all. In more significant dehydration, especially when accompanied by vomiting, poor intake, or illness, the numbers can change enough to get noticed. However, the key question is whether the change reflects simple electrolyte imbalance or a true metabolic issue.
Dehydration alone does not usually cause a major elevated anion gap. Instead, it may contribute to related problems that raise the gap, such as reduced kidney clearance, lactic acid buildup from poor perfusion, or ketone production if intake is very low. That is why a changed result should prompt the question: what is the main cause?
From a clinical perspective, dehydration can also make an already abnormal result look worse. A person with underlying illness may have borderline blood chemistry, and fluid loss can intensify the apparent abnormality. This is where careful clinical interpretation matters most.
Why Lack of hydration Might Alter Lab Results
A major way dehydration influences testing is through hemoconcentration. Once plasma water is reduced, measured substances in the blood can appear more concentrated. It can change lab values across the test panel, including sodium, chloride, bicarbonate, and other markers on a basic metabolic panel.
Another key factor is kidney function. The kidneys help control water, electrolytes, and acid-base status. If dehydration reduces kidney perfusion, the body may for a time retain waste products and alter serum chemistry. This is why BUN and creatinine are often reviewed together. A higher BUN-to-creatinine pattern can suggest volume depletion, though the overall context matters.
Dehydration can also be a clue that the body is under stress from illness, not just lacking water. For example, vomiting, fever, diarrhea, or poor intake can lead to both fluid loss and metabolic changes. In those situations, the lab pattern may reflect more than simple dehydration, and the anion gap becomes one piece of a larger puzzle.
It helps to think the result as part of an integrated review of blood chemistry. If BUN is elevated, creatinine is affected, and the anion gap is abnormal, the pattern may suggest dehydration-related strain on the kidneys or another process altogether. Here a clinician compares the numbers with symptoms and exam findings.
When a High Anion Gap Is More Worrisome
A raised anion gap is more worrisome when it suggests acid-base disturbance. This means acids are accumulating in the body more quickly than they can be eliminated or buffered. Dehydration may be present with this condition, but it is seldom the main explanation when the gap is clearly elevated.
Common causes include lactic acidosis, ketoacidosis, and poisons. Lactic acidosis can happen when tissues do not get enough oxygen or blood flow, which may occur in serious illness or marked volume depletion. Ketoacidosis can occur with diabetes, prolonged fasting, alcohol use, or very low carbohydrate intake. Certain toxins and medications can also produce a serious acid load.
These causes matter because they are true metabolic problems, not just concentration effects from dehydration. A person may be dehydrated and also have one of these conditions. In that case, the dehydration may worsen the issue, but the main concern is the core acid accumulation.
If the anion gap is high, the rest of the https://anion-gap-app151.trexgame.net/what-s-the-normal-anion-gap-range-in-adults panel becomes important. Low bicarbonate level, a changing chloride pattern, and other signs of salt imbalance can support the diagnosis. The best approach is not to focus on one number alone, but to ask whether the pattern fits a known cause of metabolic acidosis.
Low Anion Gap: Other Likely Causes
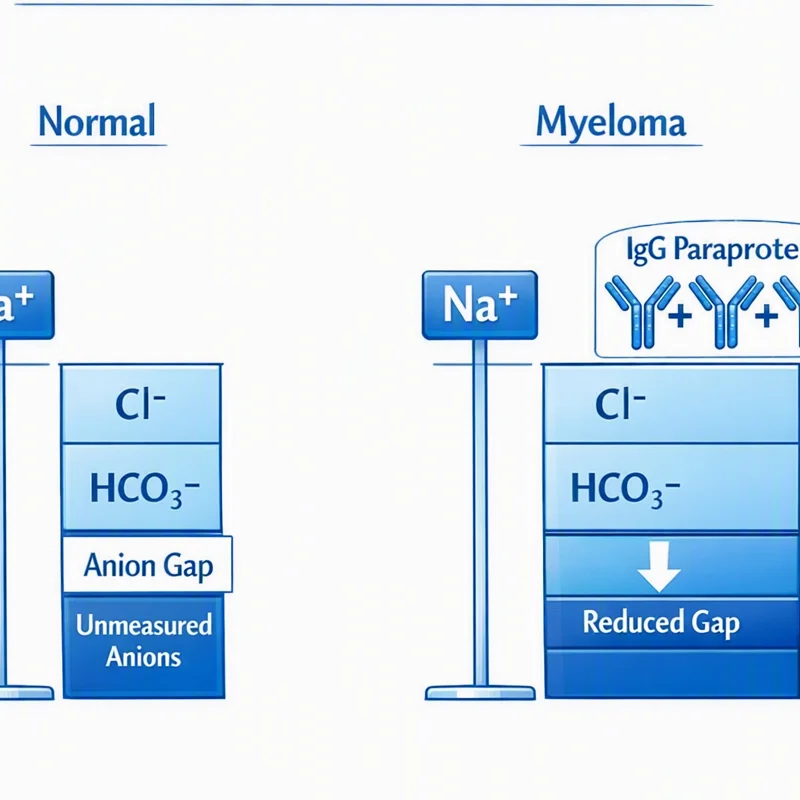
A low anion gap is not as common than a high one, and dehydration is generally not the primary cause. A leading explanation is hypoalbuminemia, since albumin is a key negatively charged protein. If albumin is decreased, the calculated gap can decrease even if there is no major acid-base disorder.
Another likely cause is multiple myeloma or other conditions that elevate abnormal proteins in the blood. These proteins may behave as positive ions or otherwise change the balance between measured and unmeasured particles. In such cases, the low gap can be a clue that more testing is needed.
Lab error is also a real possibility. Because the anion gap is calculated from several measured values, a small mistake in one input can create a misleading result. Repeating the electrolyte panel or reviewing the sample handling may help if the number does not fit the clinical picture.
When a low result appears, clinicians often review the entire basic metabolic panel, the albumin level, and any signs of protein disorders or medication effects. As with a high result, the goal is to identify the underlying cause rather than assuming the calculator result is the diagnosis.
Symptoms Needing Medical Attention
Some signs indicate that a changed anion gap may be part of a more serious illness. Confusion, rapid breathing, and vomiting can occur when the body is fighting acid-base problems or severe dehydration. Such symptoms need prompt attention, especially if they start fast or worsen.
Severe dehydration can lead to dizziness, weakness, dry mouth, very dark urine, fainting, and reduced urine output. If severe dehydration is paired with abnormal blood chemistry, the risk of kidney strain and metabolic complications increases. That is why symptom evaluation is just as important as the number itself.
Urgent or emergency care may be needed when symptoms suggest worsening acid-base imbalance, poor circulation, or inability to keep fluids down. A clinician may order repeat medical testing to check the anion gap, serum bicarbonate, kidney markers, and other data points. Symptoms together with lab results guides the next step.
If you are using an anion gap calculator and the number is abnormal, do not rely on the calculator alone if you feel unwell. Symptoms can reveal a problem that the number only hints at. In that situation, timely medical evaluation is the safest choice.
Common Questions About Dehydration and the Anion Gap
Can dehydration cause a high anion gap?
Dehydration can be associated with a high anion gap, but usually indirectly. Fluid loss can reduce blood volume, cause hemoconcentration, and contribute to kidney stress or poor tissue perfusion. Those changes may raise the gap if they lead to metabolic acidosis, lactic acidosis, or ketone buildup. Dehydration alone is not usually the full explanation.
Can dehydration cause a low anion gap?
Dehydration is not a common cause of a low anion gap. Low results are more often linked to hypoalbuminemia, multiple myeloma, lab error, or other shifts involving positive ions. If dehydration is present, it may affect lab values, but a low gap usually calls for a broader review.
What’s the normal anion gap range?
The anion gap range varies by the laboratory, the instrument, and whether albumin is considered. Many labs use a narrow expected range, but there is no single standard value. For most accurate results interpretation, check your result with the range printed on the report and review it in the context of the electrolyte test panel and blood bicarbonate.
Should I drink water before repeating an electrolyte test?
If dehydration may have affected the result, mild water intake may help rebalance fluid balance balance, but do not assume hydration alone will explain the abnormality. A repeat electrolyte panel or basic metabolic panel should be done according to the instructions from your clinician. If you have vomiting, confusion, or trouble keeping fluids down, seek medical evaluation rather than trying to self-correct the numbers.
When should a changed anion gap be evaluated by a doctor?
A changed result should be evaluated when it is clearly outside the expected expected range, when it comes with symptoms like disorientation, increased breathing rate, or throwing up, or when there are signs of severe dehydration or kidney dysfunction. A clinician may review blood urea nitrogen, serum creatinine, albumin, and the full blood chemistry to identify the root cause and decide whether more testing is needed.